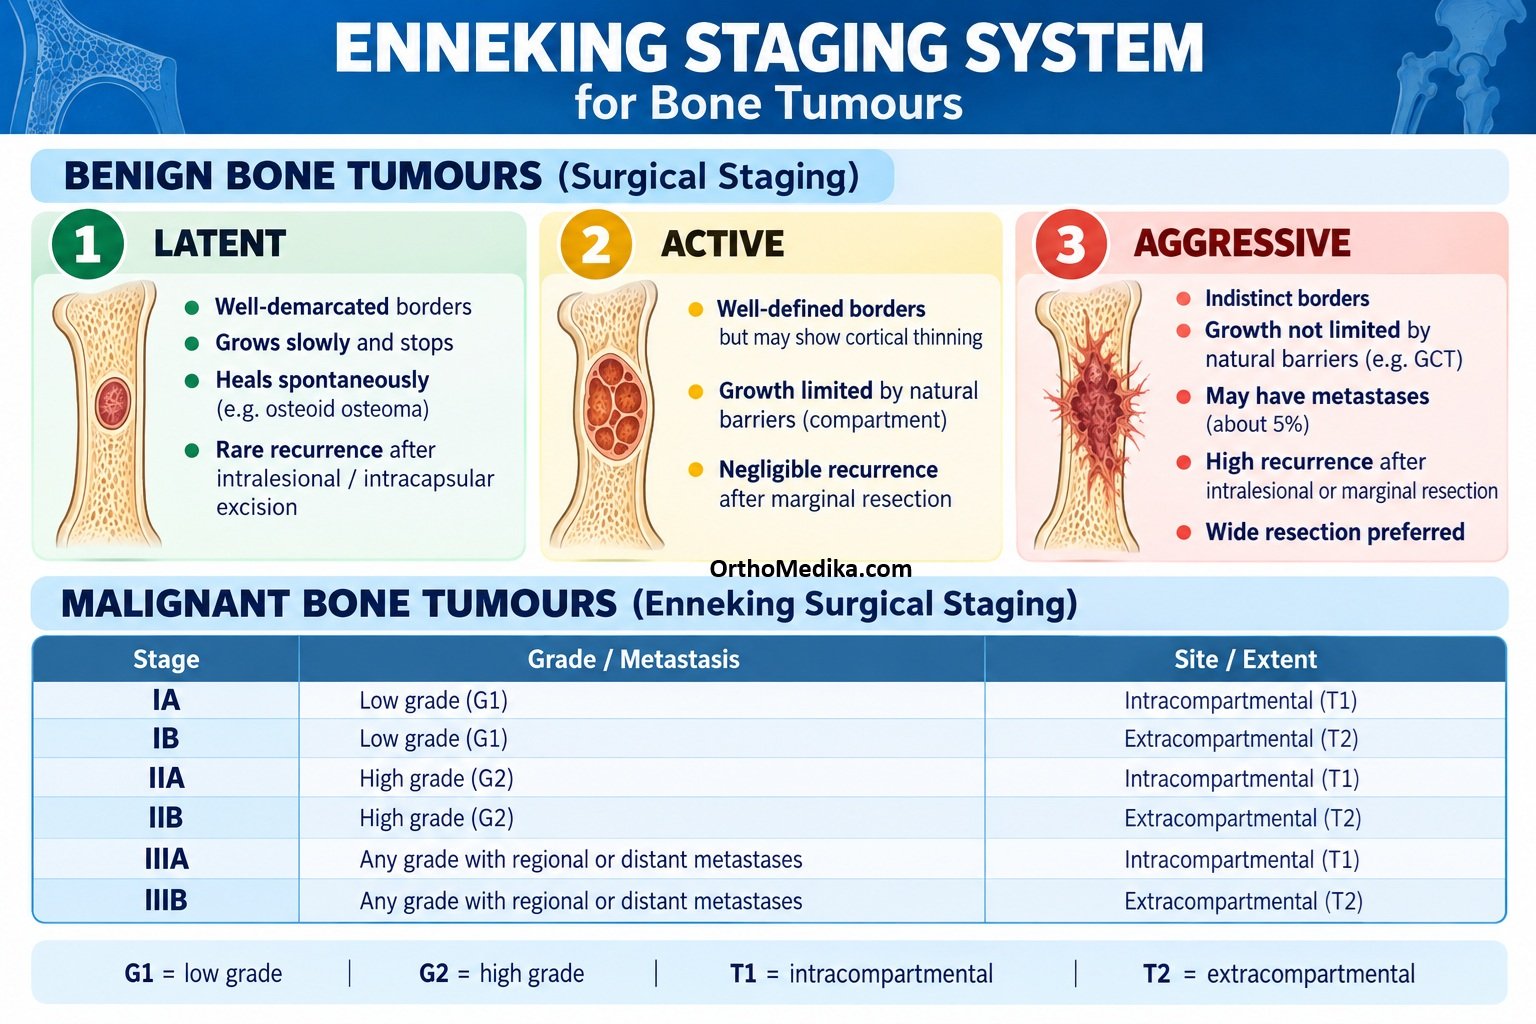
The Enneking (Musculoskeletal Tumor Society, MSTS) staging system is a widely used orthopaedic-oncology framework that stages both benign and malignant bone tumours. It combines histological grade (G), local anatomical extent (T), and metastasis (M) to predict behaviour and guide the surgical margin needed.
Core components
| Factor | Code | Meaning |
| Grade | G0 | Benign histology |
| G1 | Low-grade malignant | |
| G2 | High-grade malignant | |
| Local extent | T0 | Intracapsular/intracompartmental; well contained |
| T1 | Extracapsular but still intracompartmental | |
| T2 | Extracompartmental; has breached natural barriers | |
| Metastasis | M0 | No regional or distant metastasis |
| M1 | Regional or distant metastasis |
Grade reflects cellular aggressiveness; T is assessed mainly with MRI/CT and describes whether the tumour remains within the bone or another anatomical compartment; M records spread, most often to lung.
Benign bone tumours
Benign lesions are staged 1–3 according to clinical and radiographic aggressiveness, rather than metastatic potential.
| Stage | Name | Behaviour | Typical management |
| 1 | Latent | Well-defined, often asymptomatic, non-progressive or self-healing; intact cortex and sclerotic rim | Observe; treat only if symptomatic or at risk of fracture |
| 2 | Active | Slowly growing and symptomatic; may thin cortex but usually does not penetrate it | Intralesional curettage, often with bone graft or adjuvant |
| 3 | Aggressive | Locally destructive, indistinct margin, may breach cortex and extend into soft tissue; higher recurrence risk | More extensive curettage with adjuvants or marginal/wide excision, selected by lesion and site |
Examples: a small non-ossifying fibroma is commonly latent; an osteoid osteoma or aneurysmal bone cyst may be active; a giant cell tumour of bone is a classic aggressive benign lesion. Even stage 3 benign tumours usually do not metastasize, but they can recur locally.
Malignant bone tumours
For malignant tumours, Enneking stages are written with Roman numerals and use A/B to denote compartmental status.
| Stage | Grade | Extent | Metastasis | Practical implication |
| IA | G1 low grade | T1 intracompartmental | M0 | Lower-risk localized disease |
| IB | G1 low grade | T2 extracompartmental | M0 | Low grade but locally advanced |
| IIA | G2 high grade | T1 intracompartmental | M0 | High grade, still contained |
| IIB | G2 high grade | T2 extracompartmental | M0 | Common presentation of osteosarcoma; high local aggressiveness |
| III | G1 or G2 | T1 or T2 | M1 | Any malignant tumour with metastasis; prognosis is substantially worse |
Thus, I = low grade, II = high grade, and III = metastatic disease, while A = confined to the compartment and B = extension beyond it. A “skip lesion”—a separate tumour deposit in the same bone or across an adjacent joint—is generally treated as stage III disease.
Why it matters
The system helps surgeons choose an oncologically appropriate margin:
- Intralesional curettage: through the lesion; suitable for many latent/active benign lesions.
- Marginal excision: through the reactive zone/pseudocapsule; may be used for some aggressive benign lesions.
- Wide en-bloc resection: removes the tumour with a cuff of normal tissue; typically required for malignant lesions.
- Radical resection: removes the entire affected compartment; now less commonly used but conceptually part of the Enneking surgical-margin framework.
For example, a high-grade osteosarcoma that has broken through the femoral cortex into surrounding soft tissue but has no metastases is stage IIB; if lung metastases are present, it becomes stage III regardless of grade or local extent.
REFERENCES:
Davis JH. Anatomical classification and surgical considerations: primary spinal tumours an overview. SA orthop. j. [Internet]. 2011 Jan [cited 2026 Oct 31] ; 10( 3 ): 26-30. Available from: http://www.scielo.org.za/scielo.php?script=sci_arttext&pid=S1681-150X2011000300003&lng=en.
Springfield D, Rosen G. Staging. In: Kufe DW, Pollock RE, Weichselbaum RR, et al., editors. Holland-Frei Cancer Medicine. 6th edition. Hamilton (ON): BC Decker; 2003. Available from: https://www.ncbi.nlm.nih.gov/books/NBK12389/